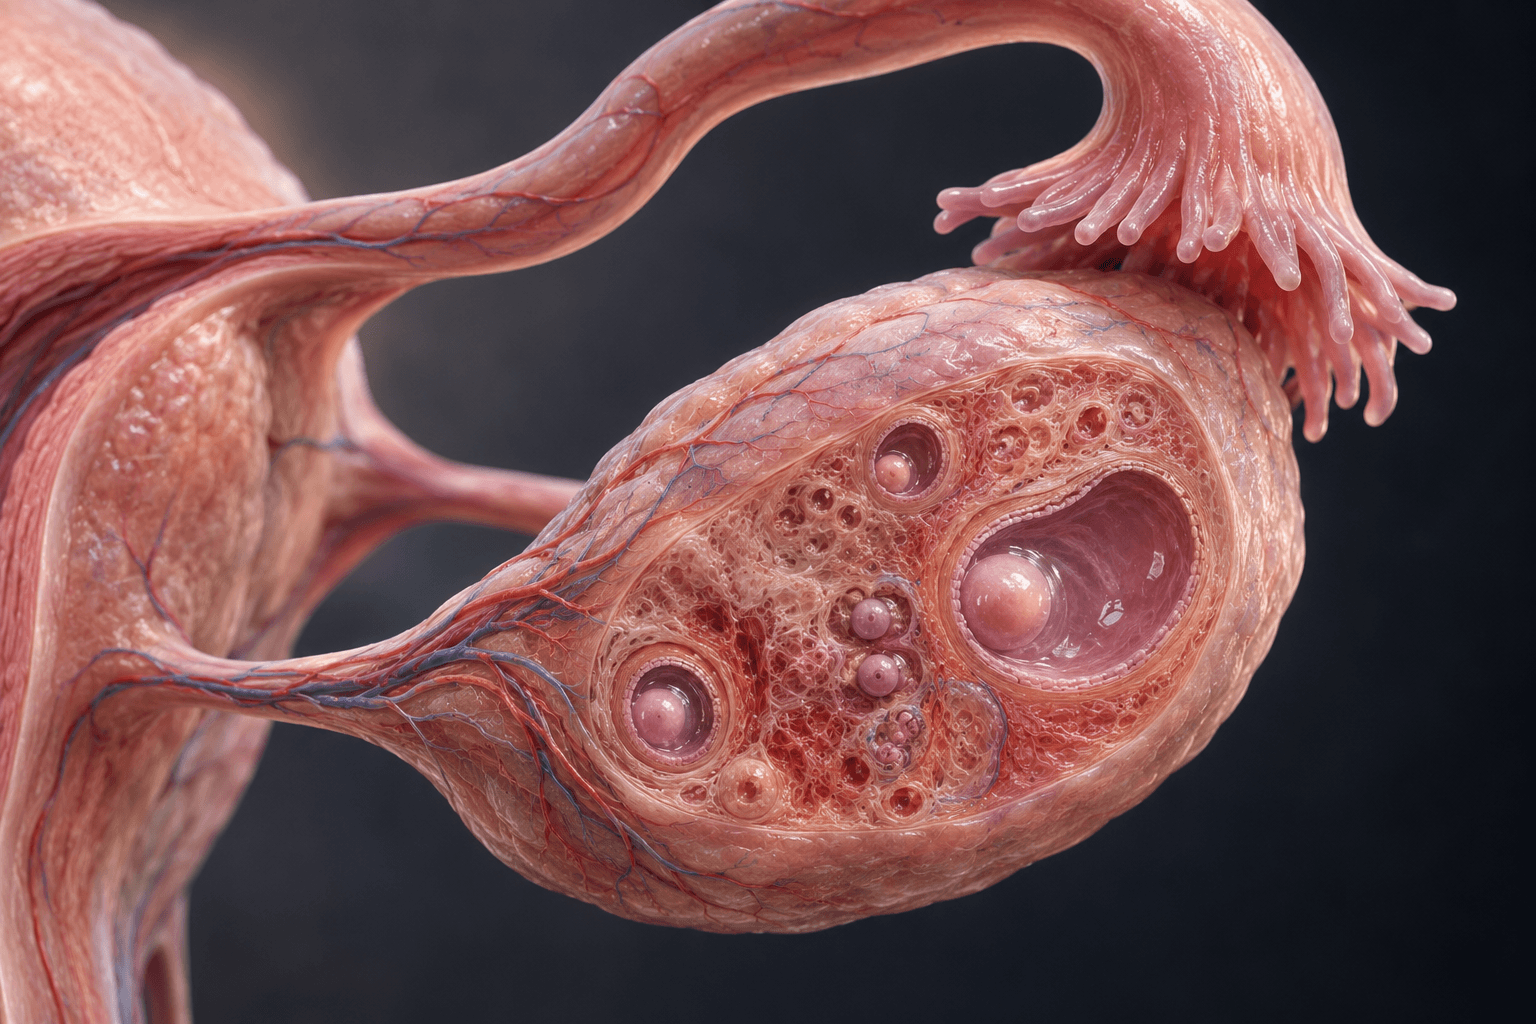
Menopause is a natural biological transition, not a disease. Still, the hormonal changes in the years leading up to it, and in the decades after, can shift your risk for several serious conditions, including heart disease, bone loss, and mood-related disorders. Much of that risk can be changed. Knowing when to act, what to watch, and how to stay in touch with your clinician leaves you better positioned than waiting for symptoms to appear.
Understanding the Transition: Perimenopause, Menopause, and Beyond
Menopause is defined as the point when a person has gone twelve consecutive months without a menstrual period, typically occurring in the early-to-mid fifties for most people in the United States. But the biological changes begin years earlier, during a phase called perimenopause, a window that can last anywhere from a few years to a decade.
During perimenopause, estrogen and progesterone levels fluctuate unpredictably before eventually declining. Those fluctuations drive the familiar symptoms, such as irregular periods, hot flashes, sleep disruption, mood changes, and brain fog. They also drive less visible shifts in cardiovascular function, bone density, and metabolic health. Postmenopause, when estrogen levels stay persistently low, is when longer-term health risks tend to settle in.
Recognizing which phase you are in matters, because some protective treatments work better, or carry a more favorable risk-to-benefit ratio, when started earlier in the transition rather than years after it has ended.
Why Timing Is More Important Than Many Realize
One of the most discussed ideas in menopause medicine over the past two decades is sometimes called the "timing hypothesis" or the "window of opportunity." Research, including large observational studies and reanalyses of clinical trial data, suggests that the cardiovascular and other effects of hormone therapy may differ depending on how soon after menopause it starts.
Starting hormone therapy closer to the onset of menopause, generally within about the first decade, appears to carry a different risk-benefit profile than starting it much later, once cardiovascular changes may already be more established. That does not mean hormone therapy is right for everyone, and it is not a decision to make without a clinician who knows your health history. It does mean the timing of these conversations with your care team matters. Waiting until symptoms become unbearable, or until years have passed, can narrow your options.
Timing also applies to screening. Bone density testing, lipid panels, blood pressure monitoring, and blood glucose checks all have windows when they are most useful. Getting baseline measurements during perimenopause gives you and your clinician a reference point that makes later changes much easier to catch and act on.
What to Track: Key Health Markers After 40
You do not need an elaborate monitoring system to stay ahead of menopause-related changes. A handful of well-established markers cover most of what matters.
- Bone density. Estrogen plays a direct role in maintaining bone mass. When estrogen declines, bone resorption can outpace bone formation, raising fracture risk over time. A DEXA scan (dual-energy X-ray absorptiometry) is the standard tool for measuring bone mineral density. Your clinician can advise on when to establish a baseline and how often to repeat it based on your personal risk factors.
- Cardiovascular markers. Before menopause, estrogen has a generally protective effect on blood vessel flexibility and cholesterol balance. After menopause, LDL ("bad") cholesterol tends to rise and HDL ("good") cholesterol may shift unfavorably. Blood pressure can also creep up. Tracking a full lipid panel and blood pressure once a year, or more often if your numbers are already borderline, lets you catch trends early.
- Blood glucose and insulin sensitivity. Metabolic changes during menopause can affect how the body processes sugar, increasing the risk of prediabetes and type 2 diabetes. A fasting glucose test or hemoglobin A1C check gives a useful window into this.
- Body composition and weight distribution. Many people notice a shift toward abdominal fat accumulation around menopause even without major changes in diet or exercise. Visceral fat (fat stored around internal organs) carries a higher metabolic risk than fat stored elsewhere. Waist circumference is a simple, low-tech marker worth tracking alongside weight.
- Mood and cognitive symptoms. Anxiety, depression, and difficulty concentrating are underreported but common during the menopause transition, and they have biological underpinnings. They are not simply a response to stress. Raising these symptoms with your clinician opens up evidence-based support, whether that is lifestyle changes, therapy, or medication.
- Sleep quality. Poor sleep is both a symptom of the menopause transition and a driver of downstream health problems including cardiovascular risk and metabolic dysfunction. If you are consistently waking due to night sweats, or experiencing insomnia unrelated to hot flashes, it is worth raising with your care team rather than accepting it as inevitable.
Lifestyle Levers That Genuinely Move the Needle
Medication and hormone therapy are only part of the picture. A consistent body of evidence points to several lifestyle factors that help offset menopause-related health risks, and that stay beneficial whether or not hormone therapy is part of the plan.
- Strength and resistance training. Weight-bearing and resistance exercise stimulates bone formation and supports muscle mass, both of which decline with age and accelerate around menopause. Aim for at least two sessions per week targeting major muscle groups, and consider working with a trainer or physical therapist initially to establish safe form.
- Aerobic exercise. Regular moderate-intensity cardiovascular activity supports heart health, helps regulate blood pressure and blood sugar, and improves sleep quality and mood. Walking briskly, swimming, cycling, and dancing all count.
- Dietary patterns. No single food prevents menopause-related disease, but dietary patterns matter. Diets rich in vegetables, legumes, whole grains, lean proteins, and healthy fats (such as those found in fish, nuts, and olive oil) are broadly supported for cardiovascular and metabolic health. Adequate calcium and vitamin D, from food or from supplements if your clinician recommends them, directly supports bone health.
- Limiting alcohol. Alcohol affects sleep quality, adds to breast cancer risk, and can worsen hot flashes in some people. If you drink, keeping intake low is a straightforward, modifiable risk factor.
- Not smoking. Smoking is associated with earlier menopause onset, lower bone density, greater cardiovascular risk, and worse symptom burden. Quitting at any point produces health benefits.
- Stress management. Chronic psychological stress elevates cortisol, which can worsen sleep, affect bone turnover, and contribute to abdominal fat accumulation. Practices like mindfulness, yoga, and social connection have evidence behind them for stress reduction.
The Follow-Up Plan: Why Ongoing Clinician Relationships Matter
One of the most useful things you can do for your menopause-related health is to establish an ongoing relationship with a clinician who takes this phase of your life seriously. That might be a primary care physician, a gynecologist, or a clinician with specialized training in menopause medicine. Some professional organizations certify clinicians specifically in this area.
Good follow-up usually includes a few things:
- Annual preventive visits that include a review of symptoms, updated biometric measurements, and age-appropriate screenings (mammography, colorectal cancer screening, and others based on your history).
- Revisiting any hormone therapy or medication plan from time to time rather than leaving it in place indefinitely. The risk-benefit balance of a treatment can shift as you move further into postmenopause.
- Speaking up when something changes. Many menopause-related symptoms are dismissed or normalized when they warrant evaluation. You are entitled to advocate for yourself, and a good care relationship makes that easier.
- Coordinating between providers if you see multiple specialists. Your primary care provider, cardiologist (if relevant), and gynecologist should ideally be working from the same picture.
A note on hormone therapy: Menopausal hormone therapy (MHT) remains one of the most effective treatments available for vasomotor symptoms like hot flashes, and it has established roles in bone protection and, in certain contexts and timings, cardiovascular health. It is also not appropriate for everyone. Whether it makes sense for you depends on your personal and family health history, the type and severity of your symptoms, your age, and how far you are from your last menstrual period. This is a conversation best had with a knowledgeable clinician, not a decision made based on headlines in either direction.
The Bottom Line
The risks that come with menopause are real, but they are also, to a large degree, manageable. The most effective approach tends to combine early awareness of what is happening and when, consistent tracking of the markers that matter most, and regular, open conversations with a clinician who treats the menopause transition as a genuine health event.
If you are in your forties or early fifties, this is a good time to start those conversations, before symptoms appear rather than after.