If you or your partner are exploring fertility, your doctor may order a semen analysis — a lab test that evaluates several characteristics of a semen sample. The report that comes back can feel like a foreign language, filled with terms like motility, morphology, and total motile count. Understanding what those terms actually mean can make a stressful conversation with a clinician feel a lot less overwhelming.
This guide walks through the three core measurements — count, motility, and morphology — explains why each matters, and describes what results outside the typical range might or might not mean for your health.
Why Semen Analysis Is Ordered
Semen analysis is usually one of the first tests recommended when a couple has been trying to conceive without success, or when a man wants a baseline picture of his reproductive health. It can also be used after a vasectomy to confirm the procedure worked.
The test is non-invasive and relatively straightforward: a sample is collected (typically through masturbation into a sterile cup) and examined under a microscope, usually within an hour of collection. Timing matters because sperm begin to change rapidly after leaving the body.
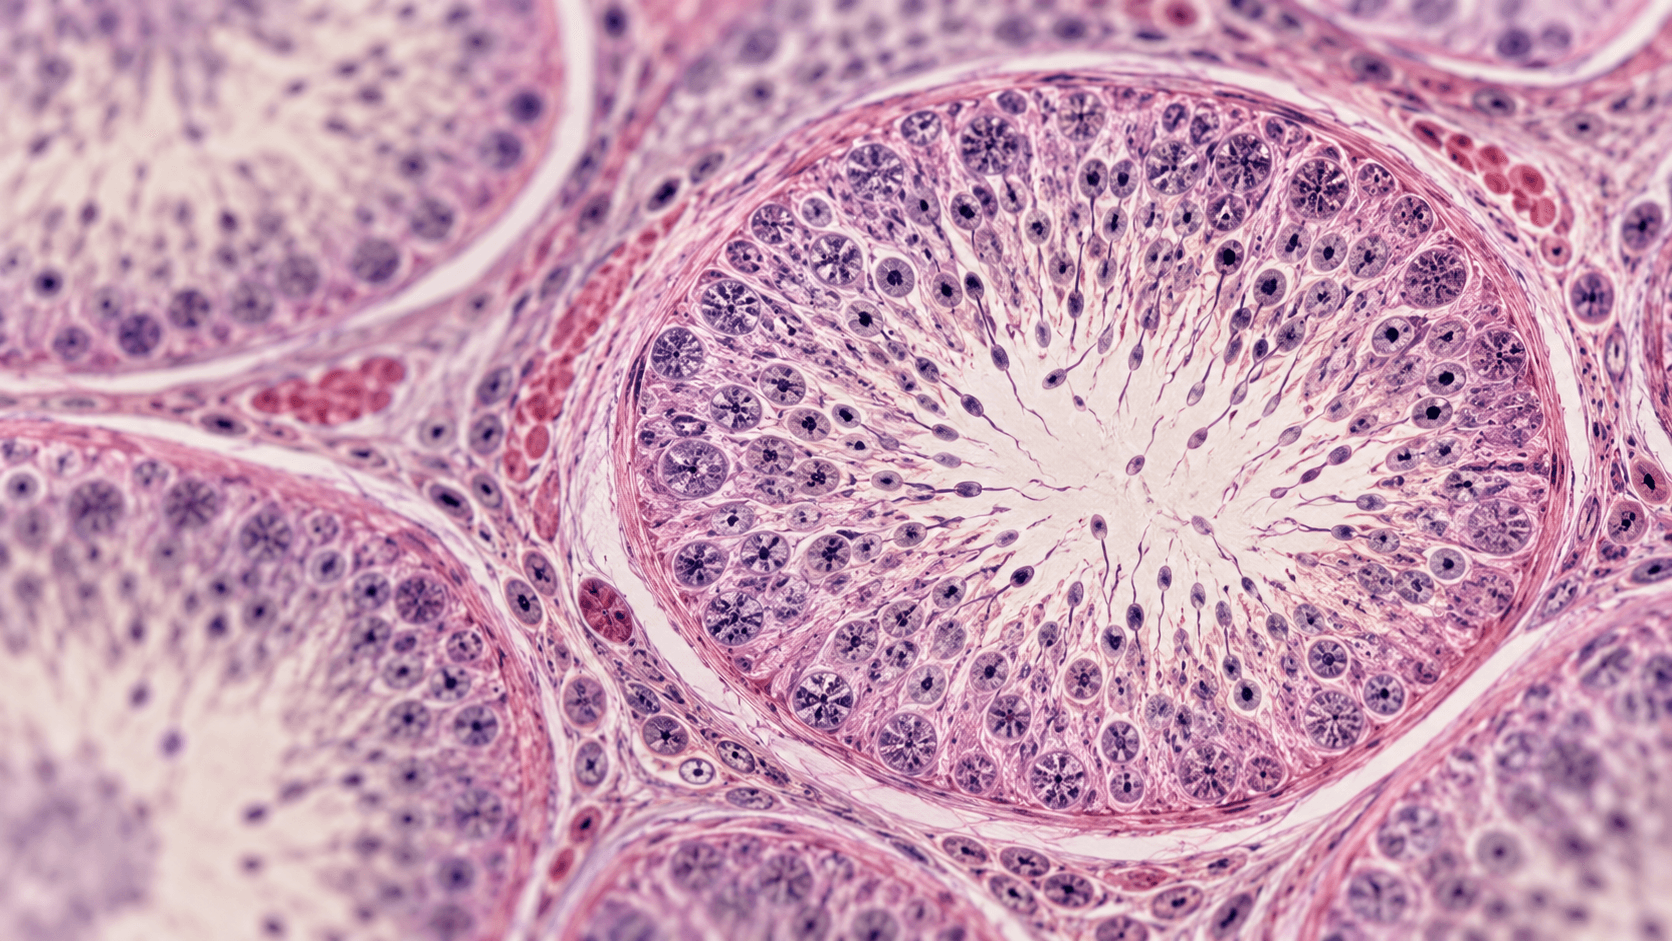
Because sperm production — a process called spermatogenesis — takes roughly two to three months to complete, a single result is a snapshot, not a permanent verdict. Many factors can temporarily affect results, which is why clinicians often recommend repeating the test before drawing conclusions.
Sperm Count: How Many Are There?
Sperm count refers to the concentration of sperm in a given volume of semen, usually reported as millions of sperm per milliliter. The report may also show total sperm count — concentration multiplied by total semen volume — which gives a fuller picture.
The World Health Organization periodically reviews population-level data and publishes reference ranges based on fertile men. Clinicians use these as general benchmarks, not absolute cutoffs. A result below the lower reference threshold is sometimes described as oligospermia (low sperm count), while the complete absence of sperm in the ejaculate is called azoospermia.
It is worth noting that count alone does not determine fertility. Men with counts below typical reference ranges have conceived naturally, and men with counts within the normal range can still face other challenges. Count is one piece of a larger picture.
Motility: Are the Sperm Moving?
Motility describes the percentage of sperm that are moving in a given sample. But not all movement is equal. Labs typically break motility into categories:
- Progressive motility: Sperm moving forward in a relatively straight line or large circle. This is the most meaningful category for fertilization, because sperm need to travel through cervical mucus, the uterus, and into the fallopian tube to reach an egg.
- Non-progressive motility: Sperm that are moving but not advancing — swimming in tight circles or twitching in place.
- Immotile: Sperm that show no movement at all.
A combined figure — total motility — adds progressive and non-progressive sperm together, though progressive motility is the number most clinicians focus on.
Low motility is called asthenospermia. When it is severe, it can make natural conception more difficult because the sperm may not be able to complete the journey to the egg. However, even samples with lower motility are sometimes used successfully in assisted reproduction, where techniques like intrauterine insemination (IUI) or in vitro fertilization (IVF) can work around some motility limitations.
Morphology: What Do the Sperm Look Like?
Morphology is arguably the most confusing result for patients to interpret, partly because the reference range looks surprisingly low at first glance.
Morphology describes the percentage of sperm with a normal shape. A typical sperm has an oval head, a well-defined midsection, and a single uncoiled tail. The lab technician uses strict criteria — most commonly the Kruger strict criteria — to score each sperm as normal or abnormal. Abnormalities can involve the head (too large, too small, two heads, irregular shape), the midsection, or the tail.
Because the scoring criteria are very precise, it is completely normal for the majority of sperm in any sample to be classified as abnormal. A result showing that a relatively small percentage of sperm are normal-shaped is considered within the acceptable range by most laboratory standards. This surprises many people, but it reflects the reality of human reproduction rather than a problem with the individual being tested.
Low morphology — called teratospermia or teratozoospermia — has been associated with longer time to conception and lower success rates with certain fertility treatments, according to research in reproductive medicine. However, the relationship between morphology and natural conception is complex, and many men with low morphology scores do conceive without assistance.
Other Things a Semen Analysis Measures
Count, motility, and morphology get the most attention, but a complete semen analysis typically includes several other values:
- Volume: The total amount of semen in the ejaculate. Very low volume may suggest a blockage or a problem with the seminal vesicles; very high volume can dilute sperm concentration.
- pH: Semen is normally slightly alkaline, which helps protect sperm from the acidic environment of the vagina. Abnormal pH can sometimes indicate infection or a structural issue.
- Liquefaction time: Semen initially forms a gel-like clot after ejaculation and then liquefies within a set window. Delayed liquefaction can affect sperm movement.
- White blood cell count: A high number of white blood cells in semen — called leukocytospermia — may signal inflammation or infection that could be affecting sperm quality.
- Total motile count (TMC): A calculated figure that combines volume, concentration, and motility to estimate the total number of forward-moving sperm in the entire sample. Many fertility specialists consider TMC one of the most practically useful numbers on the report.
What Affects These Results?
Sperm parameters are sensitive to a wide range of lifestyle, environmental, and medical factors. Some of the most well-studied influences include:
- Abstinence interval: The time since last ejaculation affects both count and motility. Labs generally recommend two to five days of abstinence before a sample to get a representative result.
- Heat exposure: The testes are located outside the body because sperm production requires a temperature slightly below core body temperature. Frequent hot tub use, prolonged laptop use on the lap, or certain occupational exposures have been studied in relation to sperm quality, with heat generally considered harmful to spermatogenesis.
- Smoking and alcohol: Observational research has linked heavy smoking and excessive alcohol use to lower sperm counts and reduced motility, though the relationship is not always straightforward.
- Body weight: Excess weight can influence hormone levels in ways that affect sperm production.
- Medications: Certain drugs — including some testosterone supplements, anabolic steroids, and specific medications used for other conditions — can significantly suppress sperm production. Always tell your doctor about everything you take.
- Illnesses and infections: A fever can temporarily reduce sperm counts for weeks afterward, because the heat affects cells already progressing through the production cycle. Sexually transmitted infections and other reproductive tract infections can also affect results.
- Stress: The evidence here is less definitive, but some research suggests that chronic psychological stress may have a modest effect on sperm parameters.
When Results Are Abnormal: What Happens Next?
An abnormal result on a single semen analysis is not a diagnosis. Because of normal biological variation and the many temporary factors that can affect sperm, most reproductive specialists will recommend repeating the test — ideally a few weeks to a couple of months after the first — before taking significant next steps.
If results are consistently outside the reference range, a urologist or reproductive endocrinologist may investigate further. This might involve a physical examination, hormone blood tests (such as FSH, LH, and testosterone), genetic testing, or imaging to look for structural issues like varicocele — a condition involving enlarged veins in the scrotum that is one of the most common correctable causes of male infertility.
Fertility treatment options range from lifestyle modifications to medical treatment of underlying conditions, to assisted reproductive technologies like IUI or IVF with intracytoplasmic sperm injection (ICSI), a technique in which a single sperm is injected directly into an egg.
A Note on Emotional Context
Receiving an abnormal semen analysis result can feel deeply personal, and it is normal to experience a range of emotions — anxiety, confusion, or grief. It is important to remember that male fertility challenges are common, that results can change over time, and that there are often multiple paths forward. Talking openly with a reproductive specialist — and, if helpful, with a counselor experienced in fertility-related stress — can make the process feel less isolating.
Semen analysis results are a starting point for a conversation, not a final answer. Your clinician is the right person to help interpret your specific numbers in the context of your overall health and your family-building goals.
Key Takeaways
- A semen analysis measures count, motility, morphology, and several other parameters that together give a picture of sperm health.
- No single number tells the whole story — results should be interpreted together and in clinical context.
- Many factors can temporarily affect results, so a single abnormal test rarely leads to a diagnosis on its own.
- Lifestyle, medications, and underlying medical conditions can all influence sperm parameters — some of which are modifiable.
- If you have questions about your results, a reproductive urologist or reproductive endocrinologist is the most appropriate specialist to consult.